Falcon Xpress

Portable Physiologic Vascular Testing Systems Without Compromise

Portable Physiologic Vascular Testing Systems Without Compromise

Advanced Vascular Testing Wherever It’s Needed

The Falcon Xpress by Viasonix sets a new benchmark in peripheral vascular diagnostics. Whether you’re conducting ABI, TBI, segmental studies, venous reflux, or advanced protocols like PWV, fistula steal, and post-exercise testing, Falcon Xpress provides comprehensive, customizable, and efficient solutions. Built with advanced IPU technology, full-color Doppler spectral display, and time-saving automation tools, the Xpress ensures accuracy, speed, and reliability in any clinical setting.

Designed for Mobility Without Sacrificing Clinical Performance

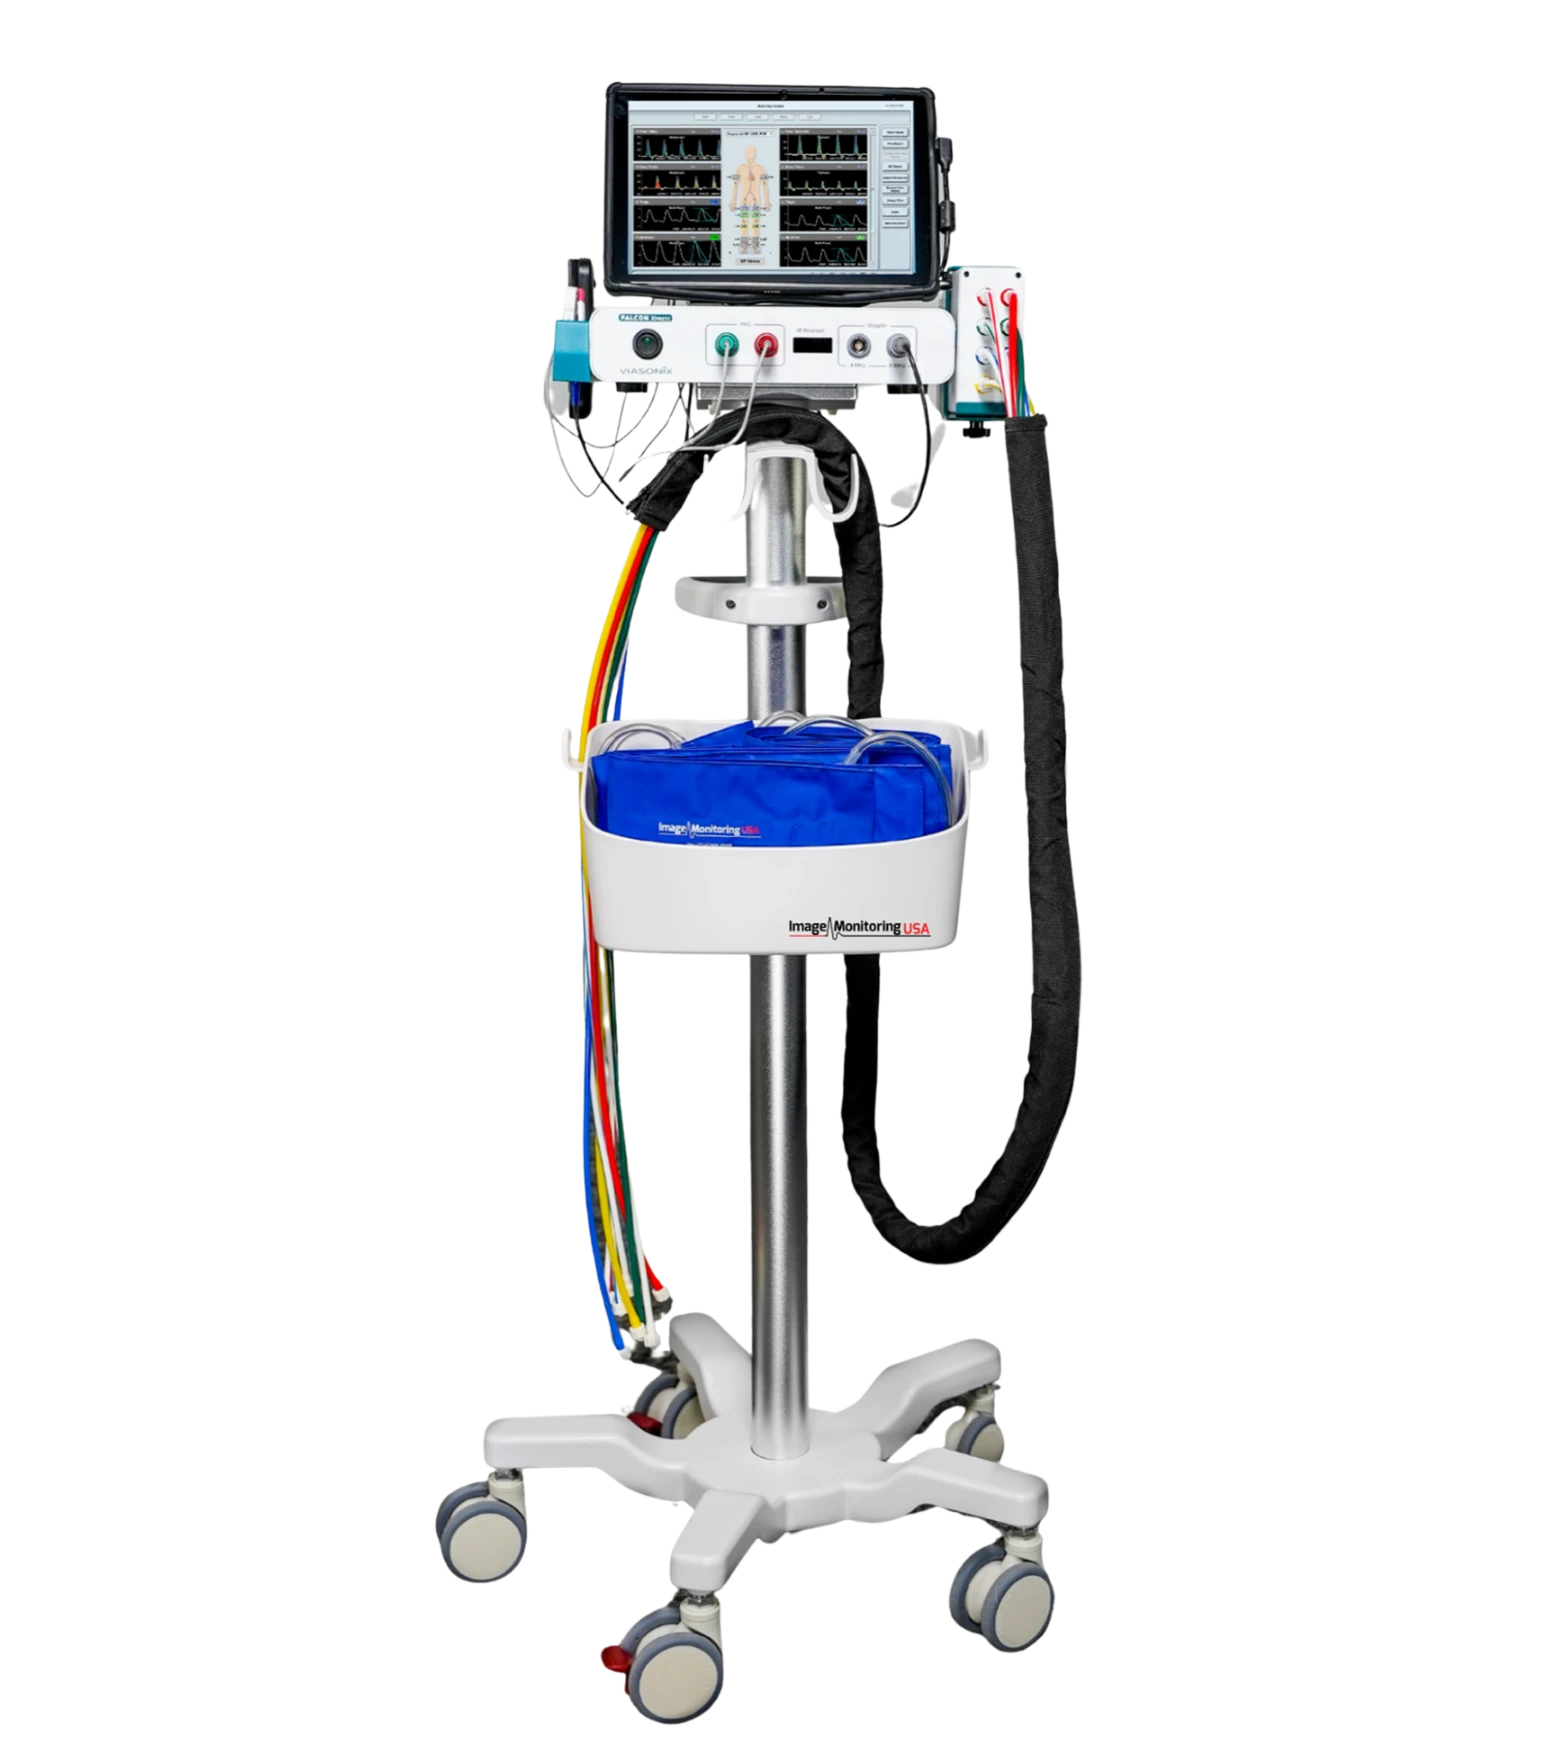
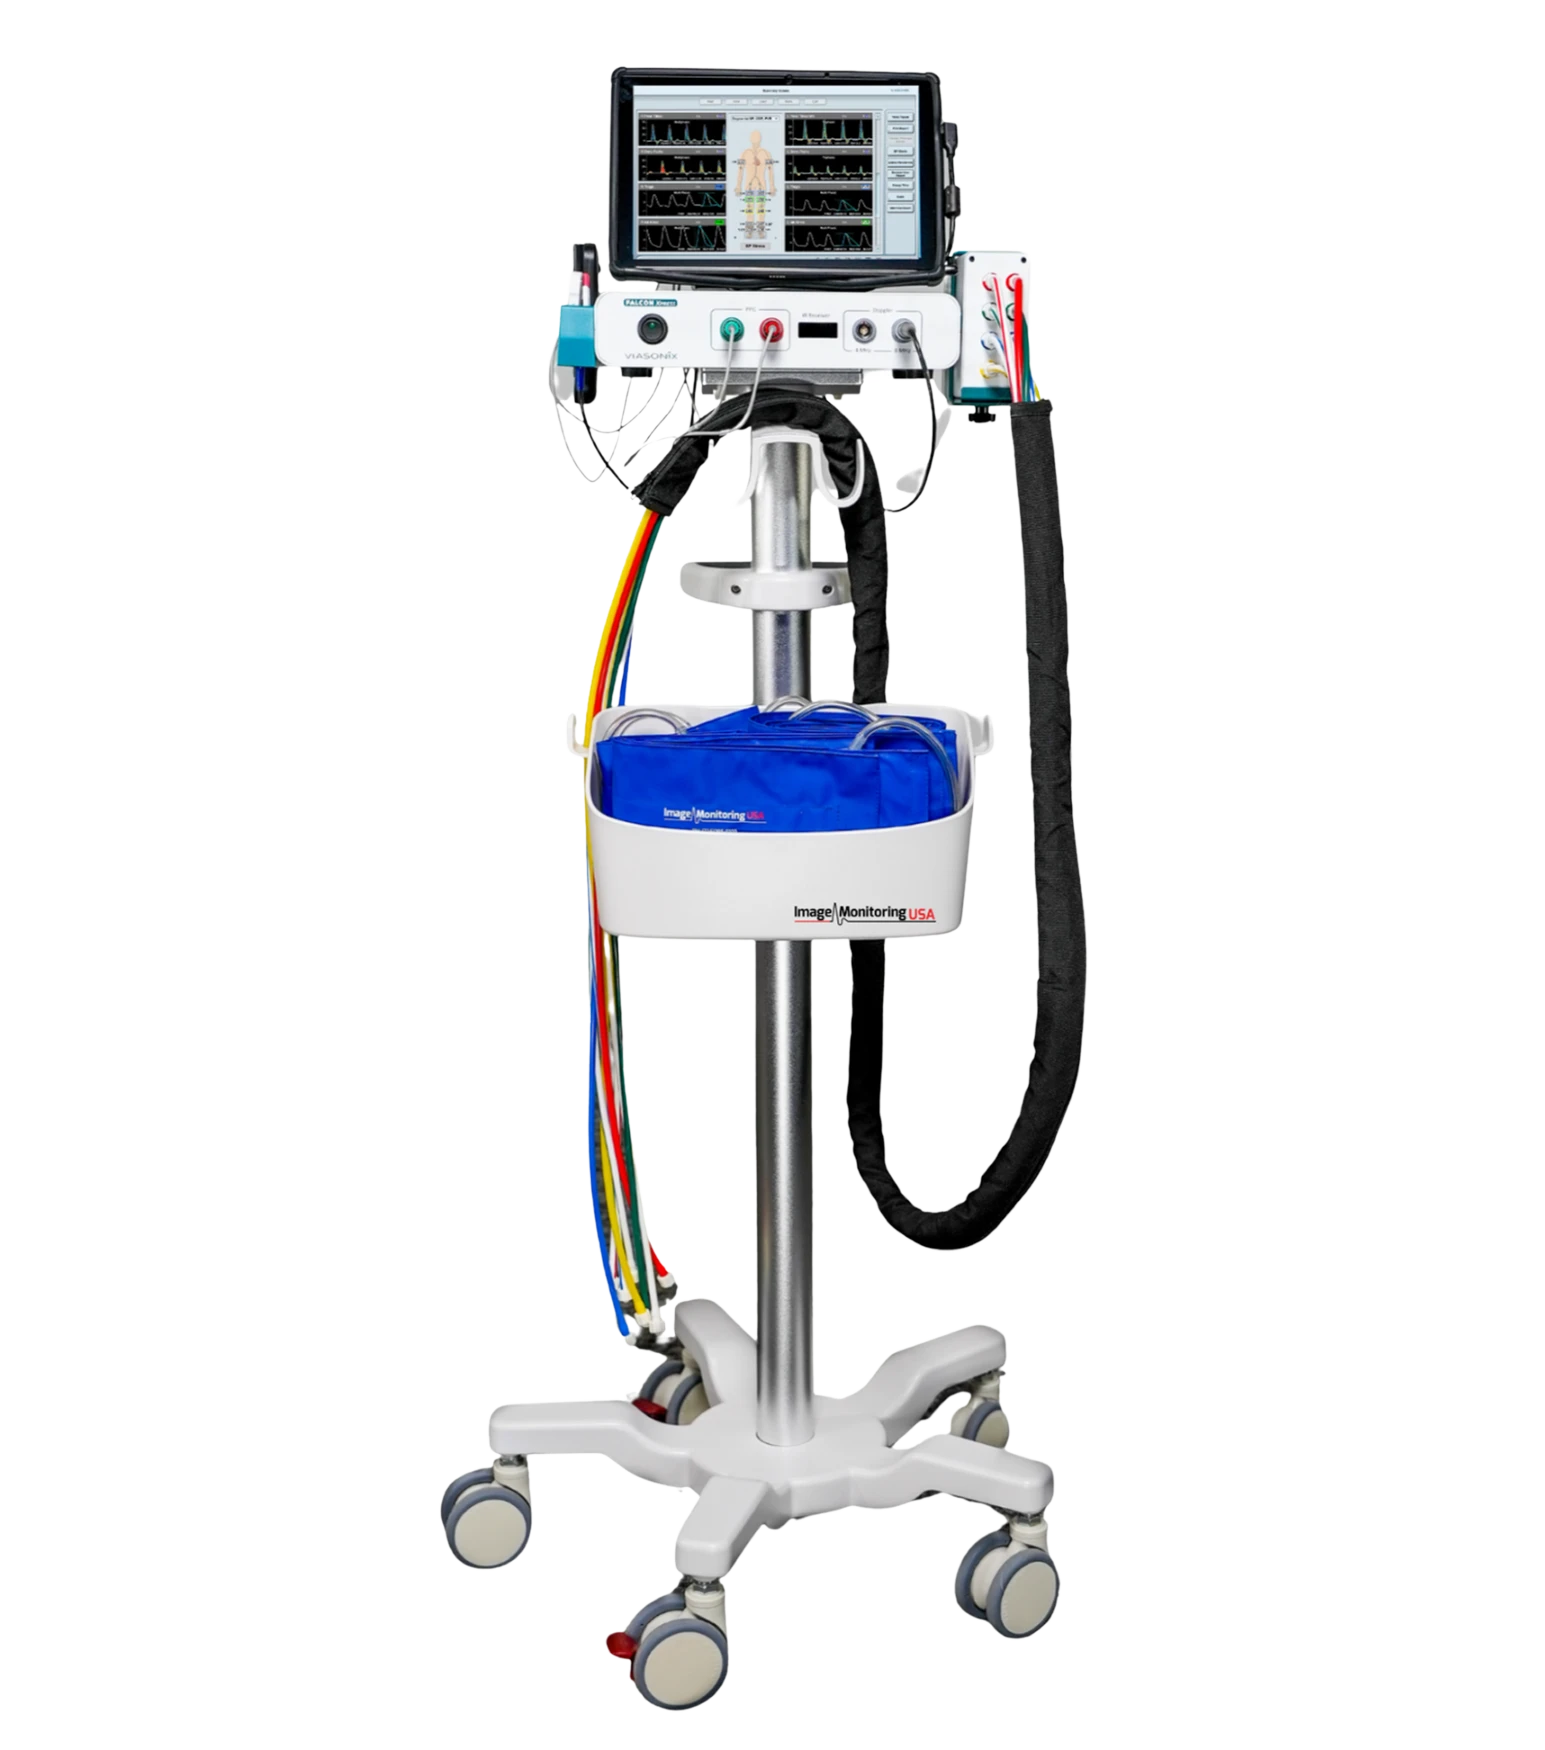
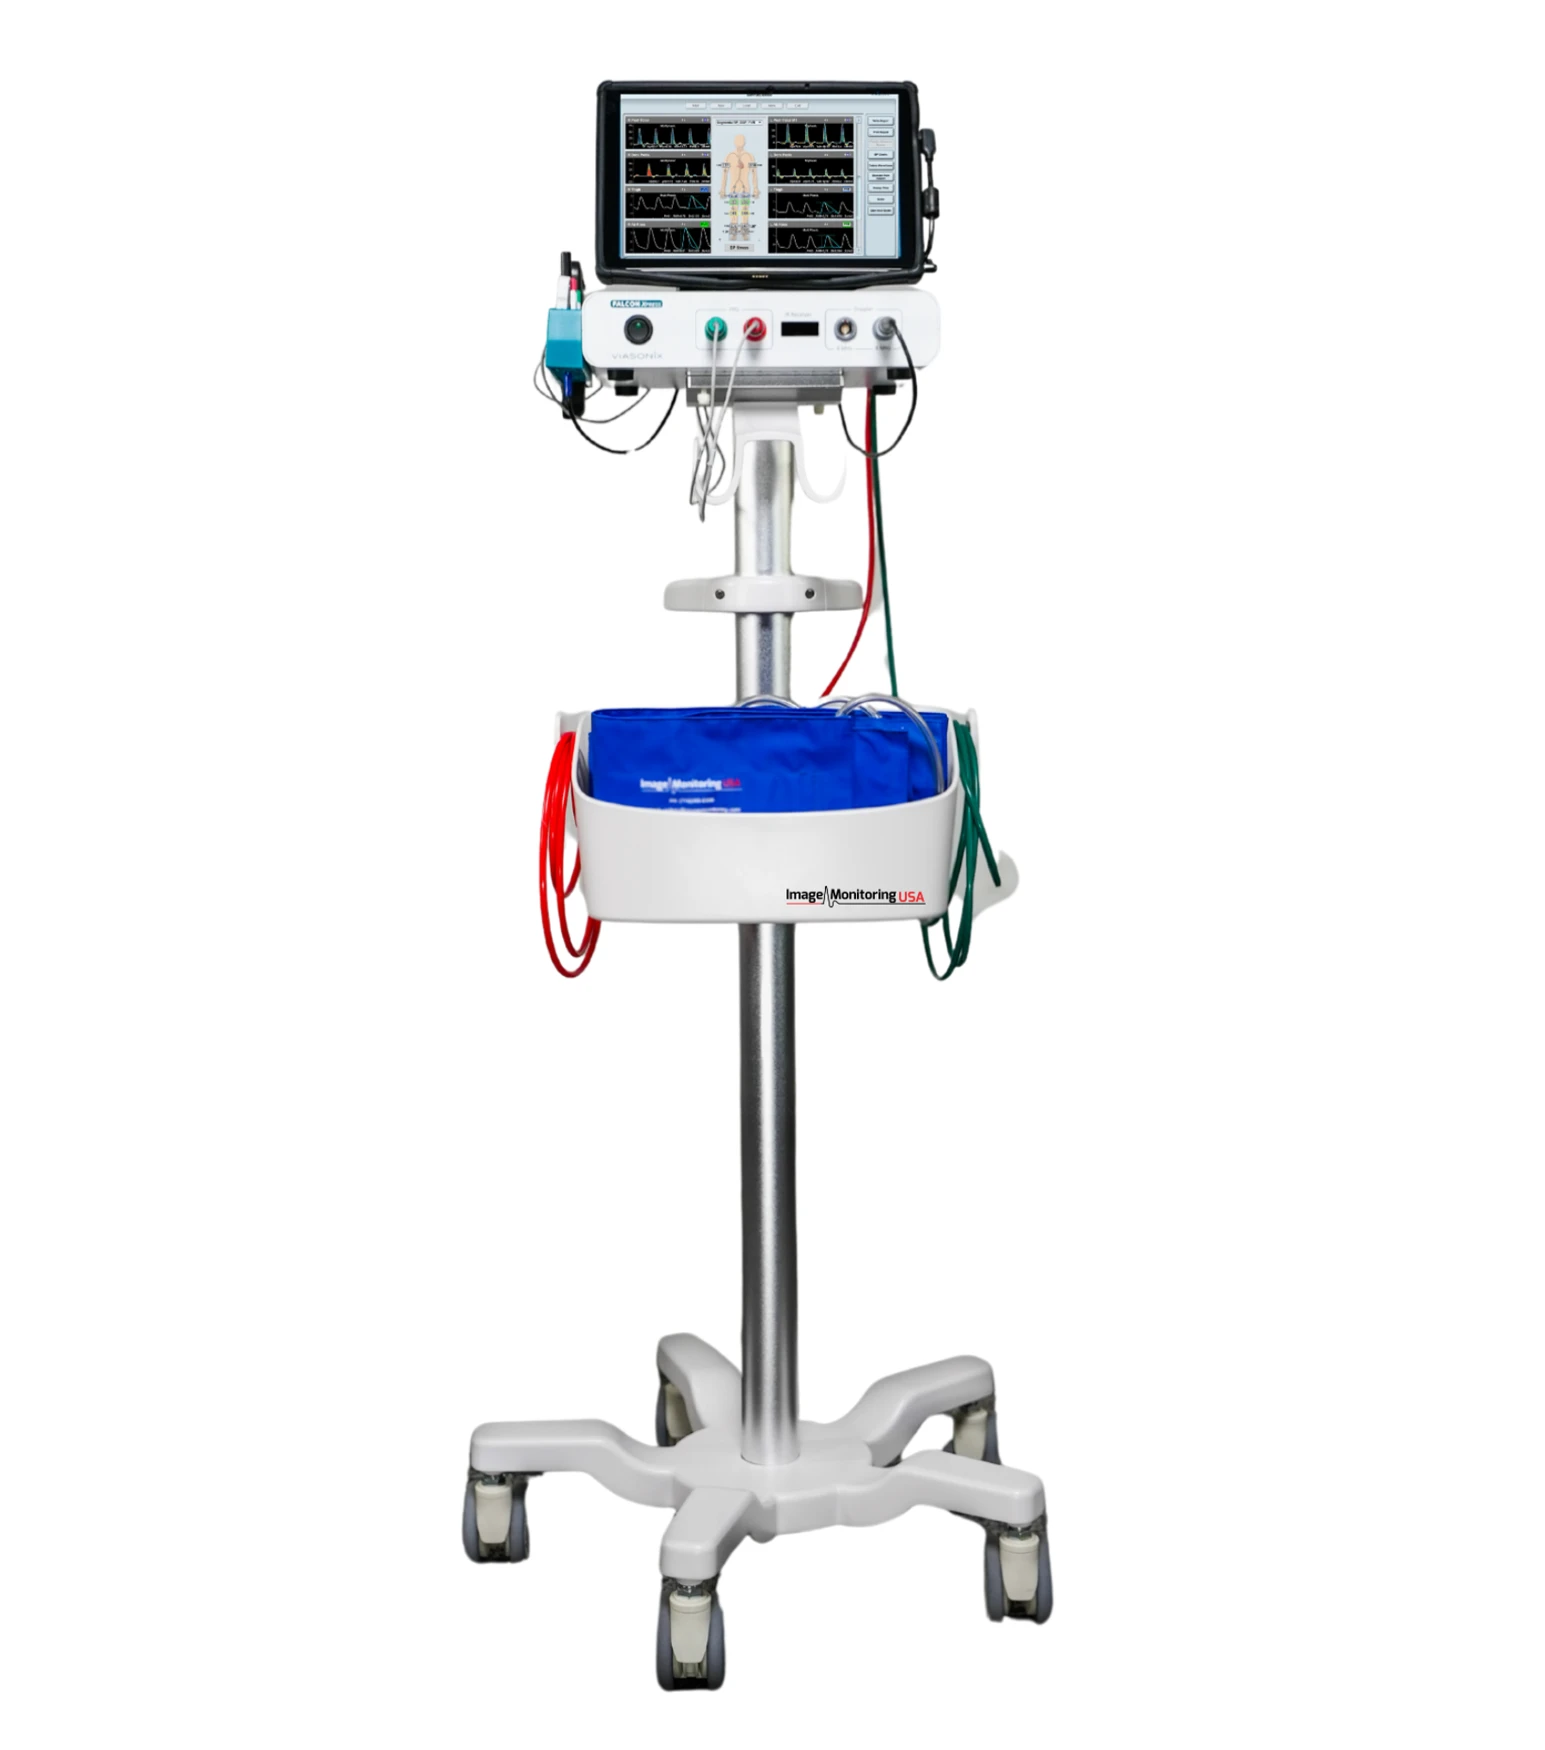
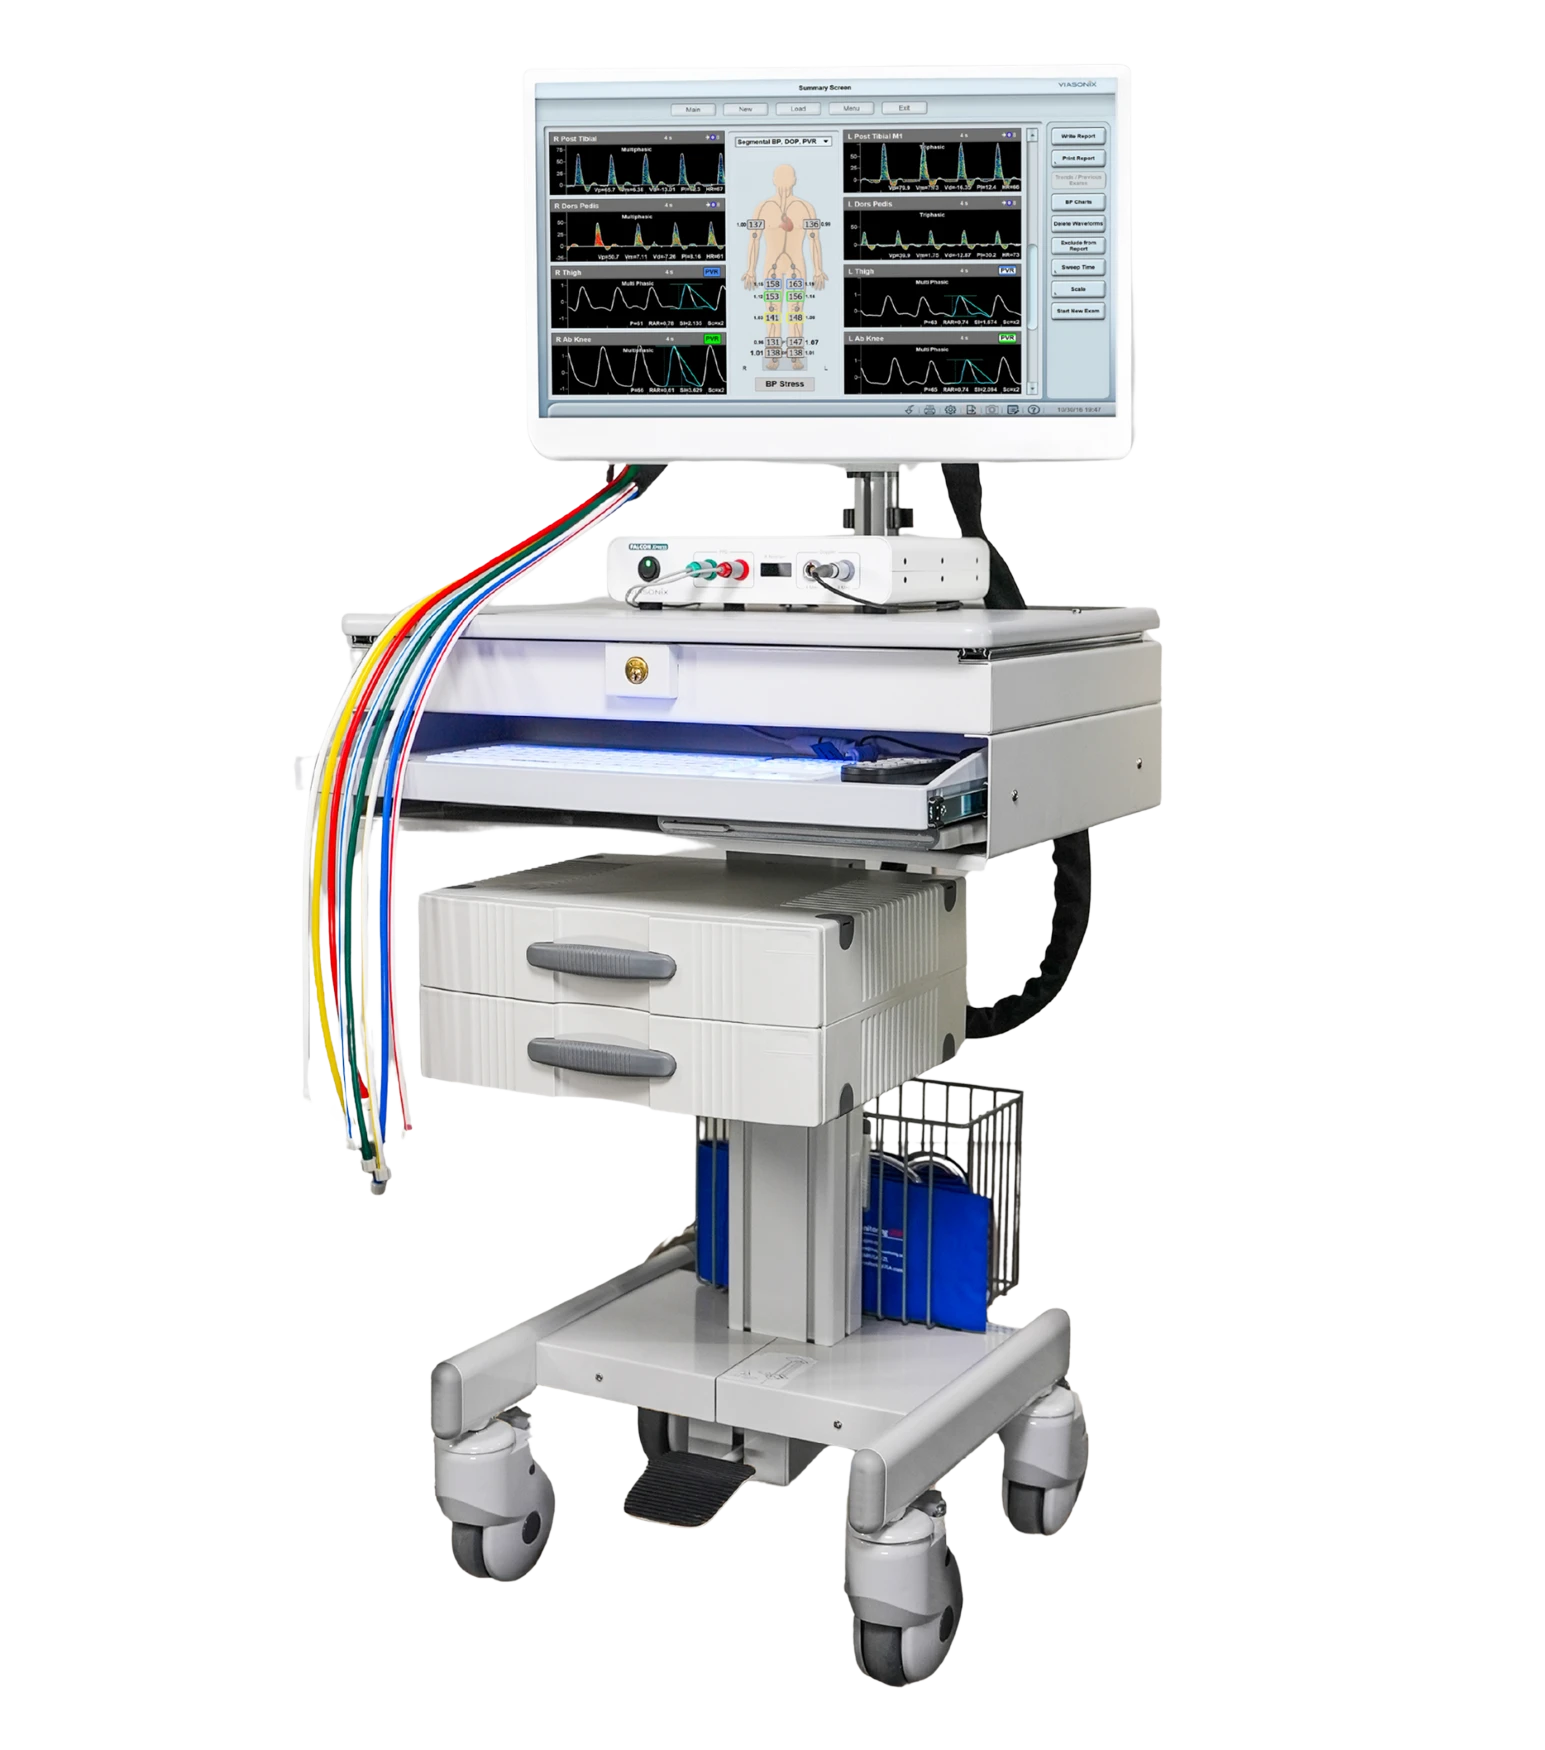
The Falcon Xpress was built with mobility in mind—perfect for clinics, outpatient centers, bedside testing, or mobile diagnostic services. With compact configurations, pole carts, and even laptop or tablet-based setups, the Xpress is easy to transport and quick to set up in any environment. Whether you’re moving between exam rooms or bringing diagnostics directly to patients, the Falcon Xpress offers seamless portability without sacrificing performance, making it the ideal solution for multi-site practices and on-the-go vascular testing.

Multiple models and configurations available:

For Office Use

Mobile – On the Go
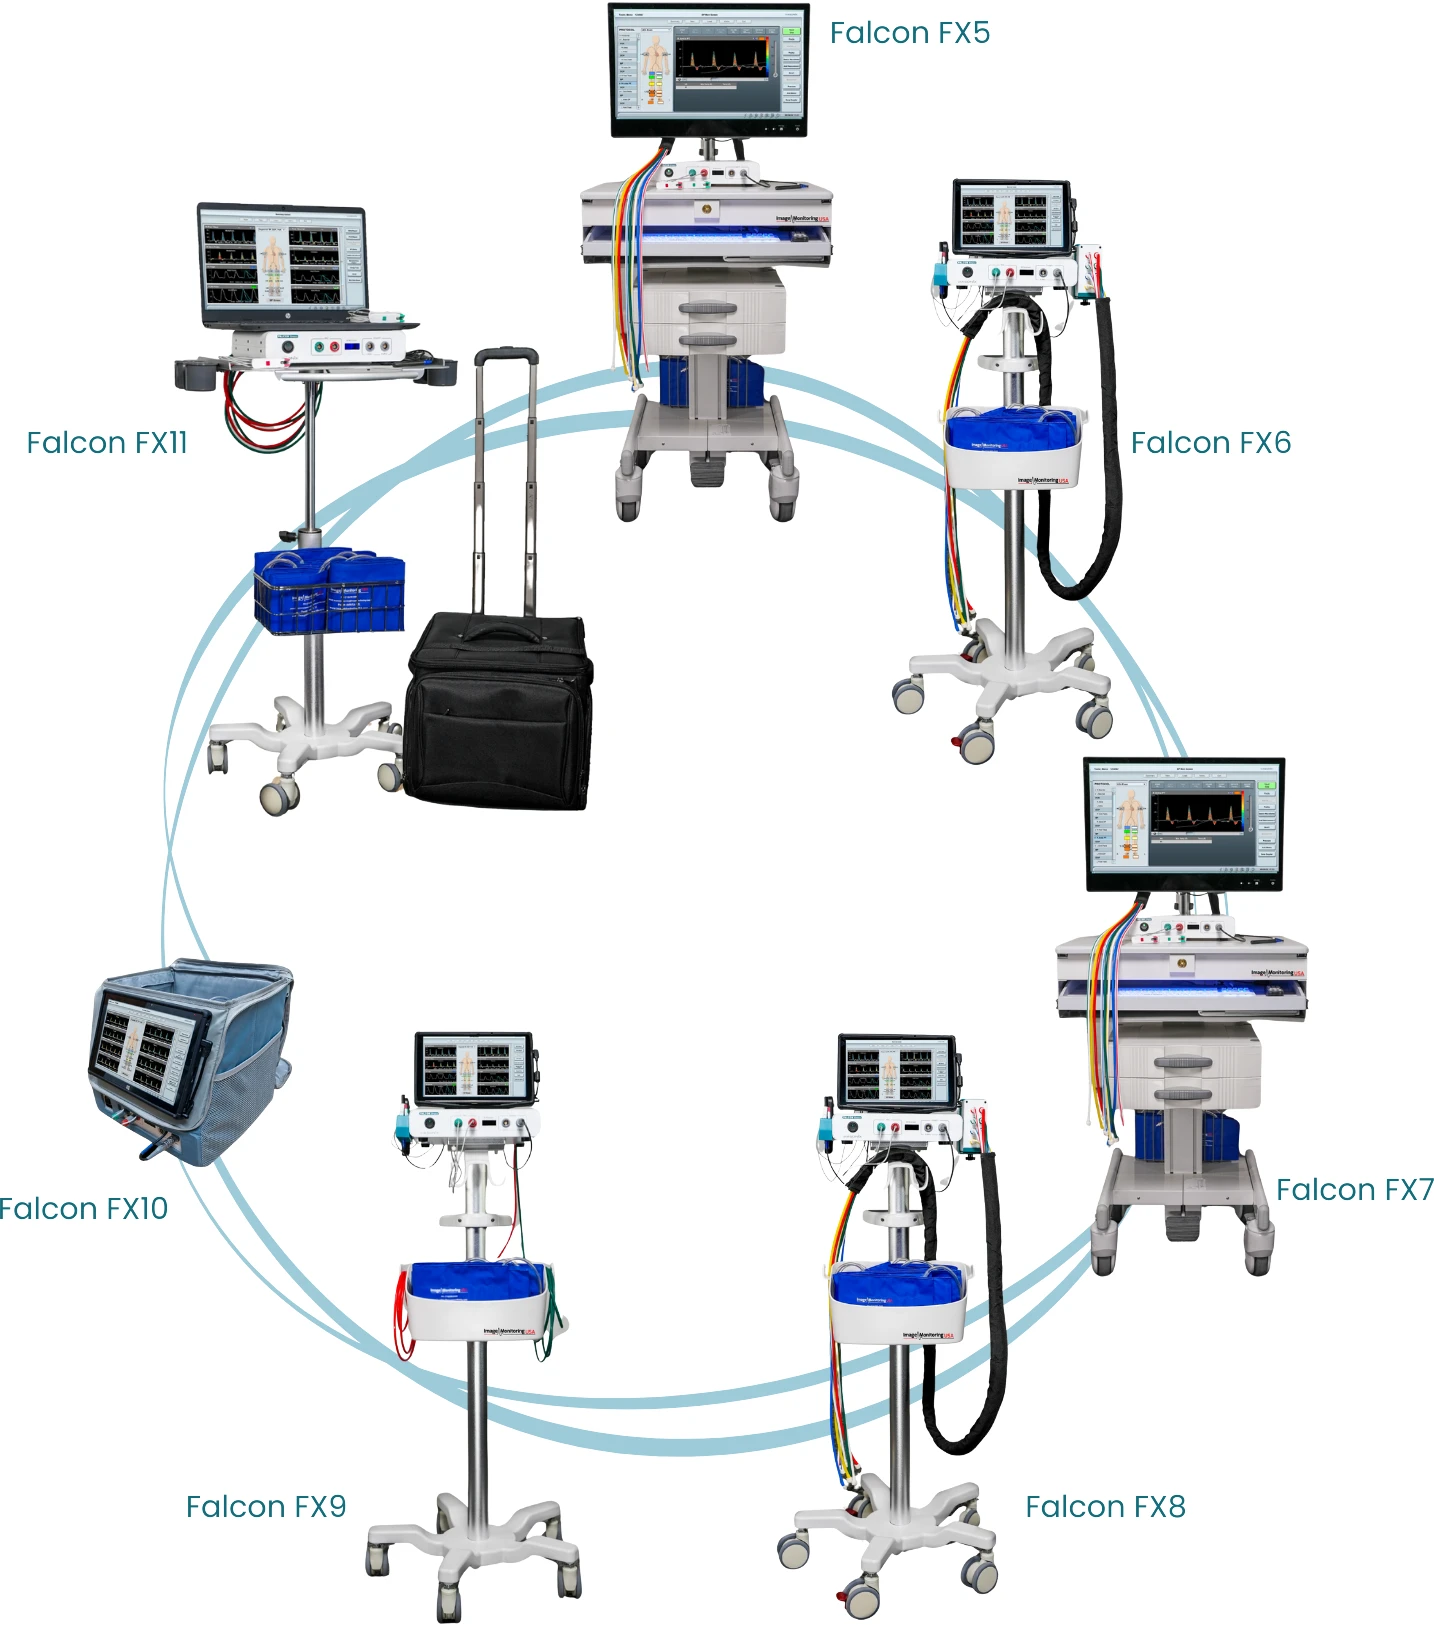
Compare Models

Us our comparison chart to find the Falcon Xpress system best suited to your needs.

Designed for Mobility Without Sacrificing Clinical Performance

The Falcon Xpress was built with mobility in mind—perfect for clinics, outpatient centers, bedside testing, or mobile diagnostic services. With compact configurations, pole carts, and even laptop or tablet-based setups, the Xpress is easy to transport and quick to set up in any environment. Whether you’re moving between exam rooms or bringing diagnostics directly to patients, the Falcon Xpress offers seamless portability without sacrificing performance, making it the ideal solution for multi-site practices and on-the-go vascular testing.

Multiple models and configurations available:

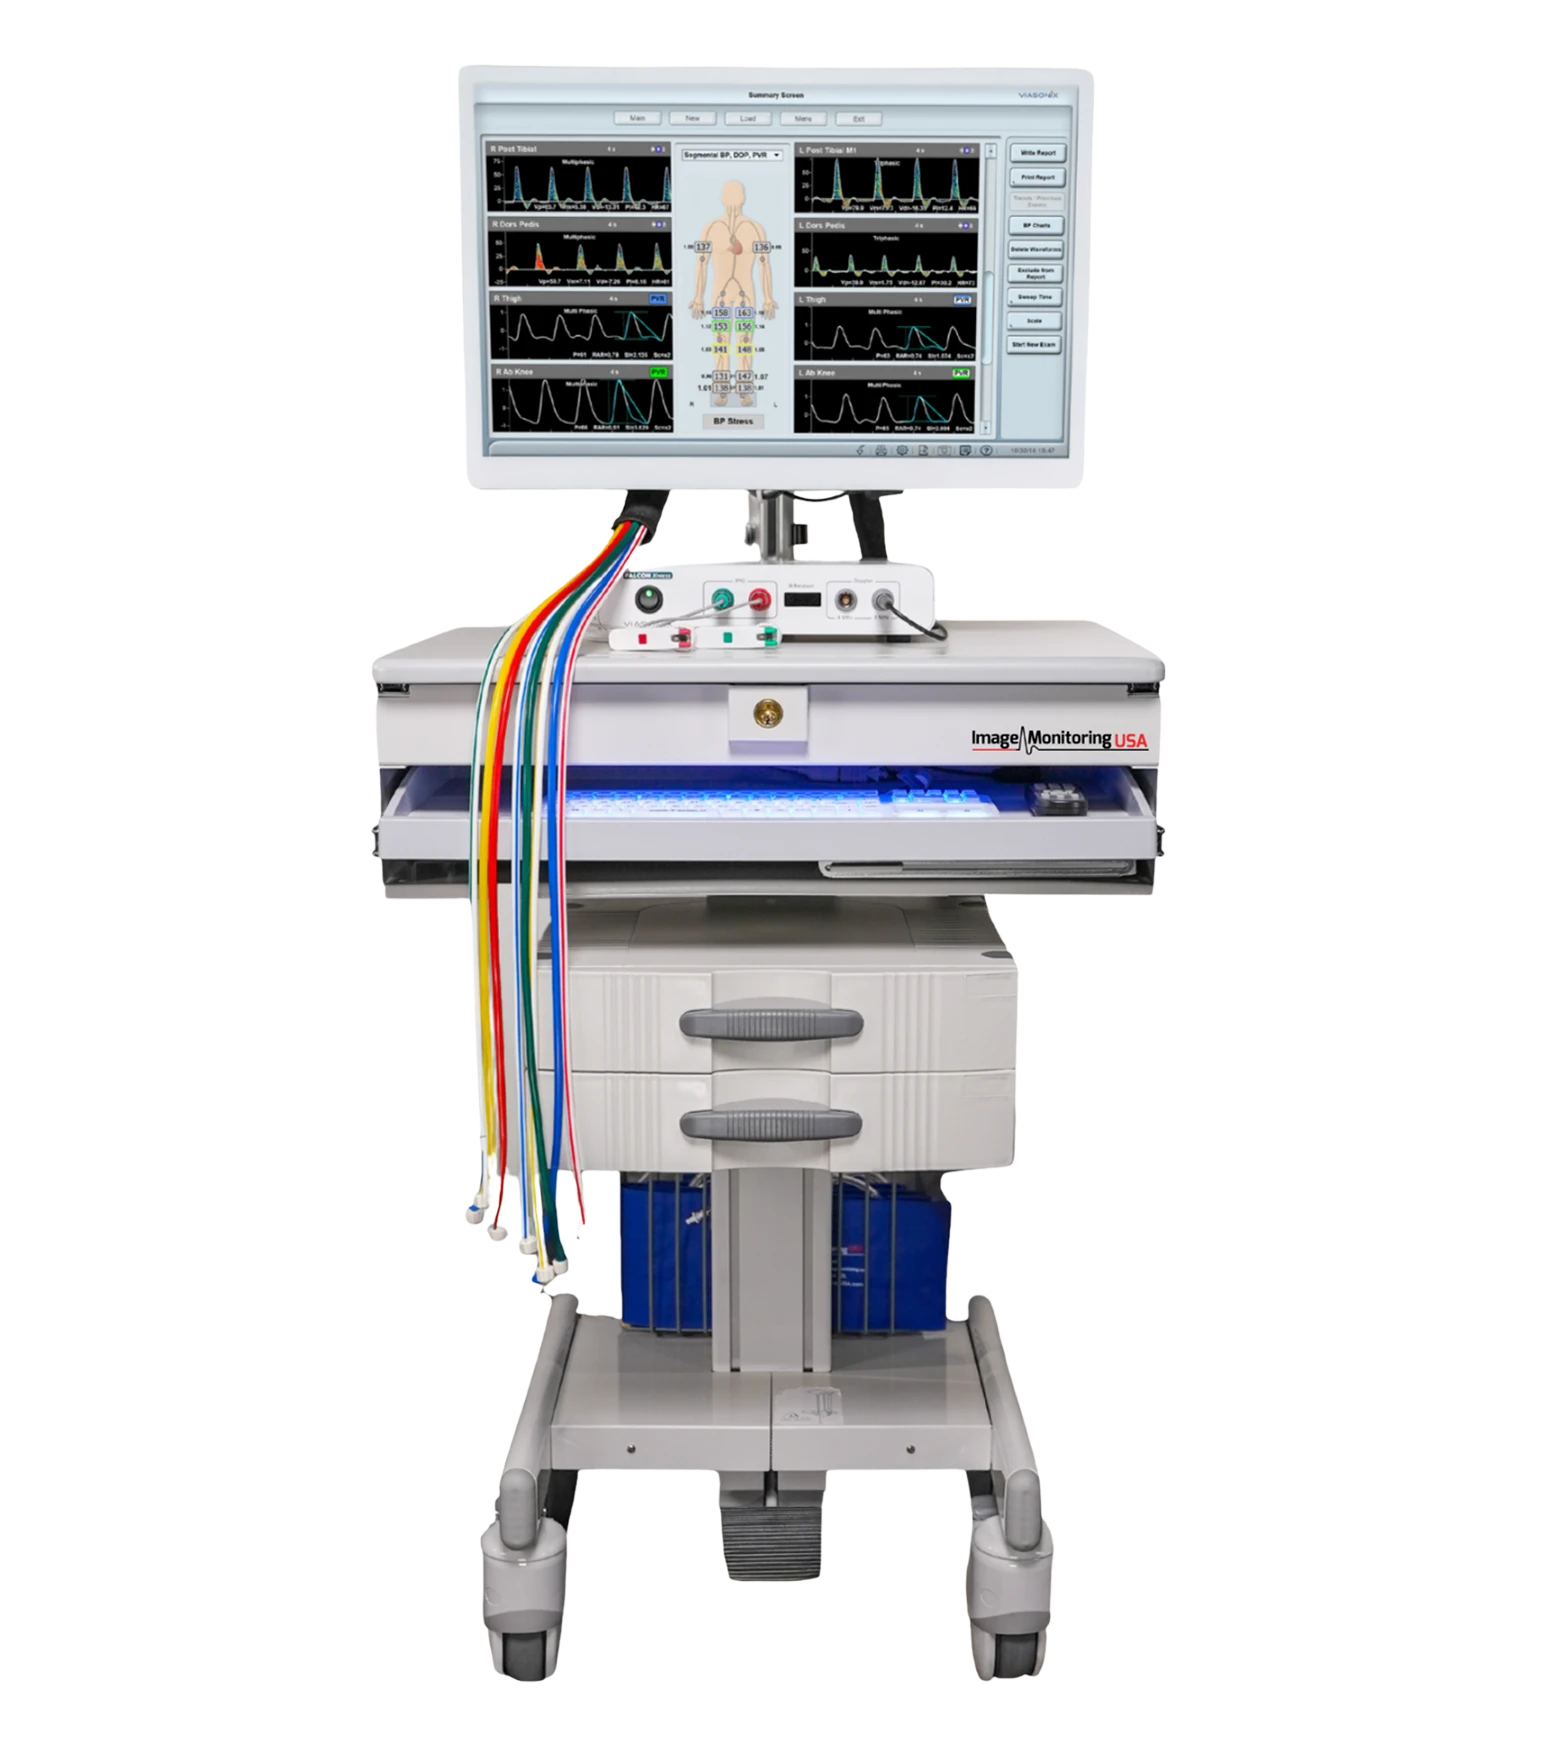
For Office Use

  • Falcon Xpress Module
  • 8MHz Spectral Doppler Probe
  • Two UltraSense PPGs with Removable Clips
  • Auto PVR with post processing capabilities
  • Premium Falcon Software – Fully Customizable Protocols, Full Lower and Upper Arterial Physiologic Testing including TOS, Fistula Steal, Palmar Arch, Full Segmental, PostExercise, TBI, Venous reflux
  • 8 Hose Automatic Cuff Selector
  • DICOM/DICOM SR
  • Wireless Remote with built-in IR Sensor
  • Seal Shield Keyboard
  • Sit-Stand Mobile Office Base Medical System Cart with Drawer & Computer mount.
  • 19” Touch Screen All in one Office Computer. Windows 11 OS
  • Falcon Xpress Module
  • 8MHz Spectral Doppler Probe
  • Two UltraSense PPGs with Removable Clips
  • Auto PVR with post processing capabilities
  • Premium Software – Fully Customizable Protocols. Full Lower and Upper Arterial Physiologic Testing including TOS, Fistula Steal, Palmar Arch, Full Segmental, Post Exercise, TBI
  • 8 Hose Automated Cuff Selector
  • DICOM/DICOM SR
  • Wireless Remote with built-in IR Sensor
  • Xpress Keyboard
  • Falcon Xpress Pole Cart
  • Touchscreen Tablet, Tablet Hub/Holder and 1-hour rechargeable battery
  • Falcon Xpress Module
  • 8MHz Spectral Doppler Probe
  • Two UltraSense PPGs with Removable Clips
  • Auto PVR with post processing capabilities
  • Standard Software -One Configurable  Protocol for ABI, TBI, Segmental, Post Ex., Non-Configurable Fixed Protocols: TOS, Fistula Steal, Palmar Arch, Upper Arterial, Venous Reflux
  • 8 Hose Automatic Cuff Selector
  • Wireless Remote with built in IR Sensor
  • Seal Shield Keyboard
  • Sit-Stand Mobile Office Base Medical System Cart with Drawer & Computer mount
  • 19” Touch Screen All in one Office Computer. Windows 11 OS
  • DICOM/DICOM SR Optional
  • Falcon Xpress Module
  • 8MHz Spectral Doppler Probe
  • Two UltraSense PPGs with Removable Clips
  • Auto PVR with post processing capabilities
  • Standard Software -One Configurable Protocol for ABI,TBI, Segmental, Post Ex. Non-Configurable Fixed Protocols: TOS, Fistula Steal, Palmar Arch, Upper Arterial, Venous Reflux
  • 8 Hose Automatic Cuff Selector
  • Falcon Xpress Pole Cart
  • Xpress Keyboard
  • Wireless Remote with built in IR Sensor
  • Touchscreen Tablet, Tablet Hub/Holder and 1-hour rechargeable battery
  • DICOM/DICOM SR Optional

Mobile – On the Go

  • Falcon Xpress Module
  • 8MHz Spectral Doppler Probe
  • Two UltraSense PPGs with Removable Clips
  • Auto PVR with post processing capabilities
  • Standard Software -One Configurable Protocol for ABI, TBI,Segmental, Post Ex. Non-Configurable Fixed Protocols: TOS,Fistula Steal, Palmar Arch, Upper Arterial, Venous Reflux
  • DICOM/DICOM SR
  • Falcon Xpress Pole Cart
  • Xpress Keyboard
  • Wireless Remote with built in IR Sensor
  • Touchscreen Tablet, Tablet Hub/Holder and 1-hour rechargeable battery
  • Falcon Xpress Mobile
  • 8MHz Spectral Doppler Probe
  • Two UltraSense PPGs with Removable Clips
  • Auto PVR with post processing capabilities
  • Standard Software -One Configurable Protocol for ABI, TBI,Segmental, Post Ex. Non-Configurable Fixed Protocols: TOS,Fistula Steal, Palmar Arch, Upper Arterial, Venous Reflux
  • DICOM/DICOM SR
  • Falcon Xpress Bag
  • Wireless Remote with built in IR Sensor
  • Touchscreen Tablet, Custom Xpress Bag with TabletHolder/Hub and 1-hour rechargeable battery
  • Falcon Xpress Module
  • 8MHz Spectral Doppler Probe
  • Two UltraSense PPGs with Removable Clips
  • Auto PVR with post processing capabilities
  • Standard Software -Limited One Configurable Protocol for ABI,TBI, Segmental, Post Ex. Non-Configurable Fixed Protocols: TOS,Fistula Steal, Palmar Arch, Upper Arterial, Venous Reflux
  • DICOM/DICOM SR
  • Wireless Remote with built in IR Sensor
  • Laptop with Roller Bag
  • Package Pole Cart Optional

Compare Models

Download our comparison chart to find the Falcon Xpress system best suited to your needs.
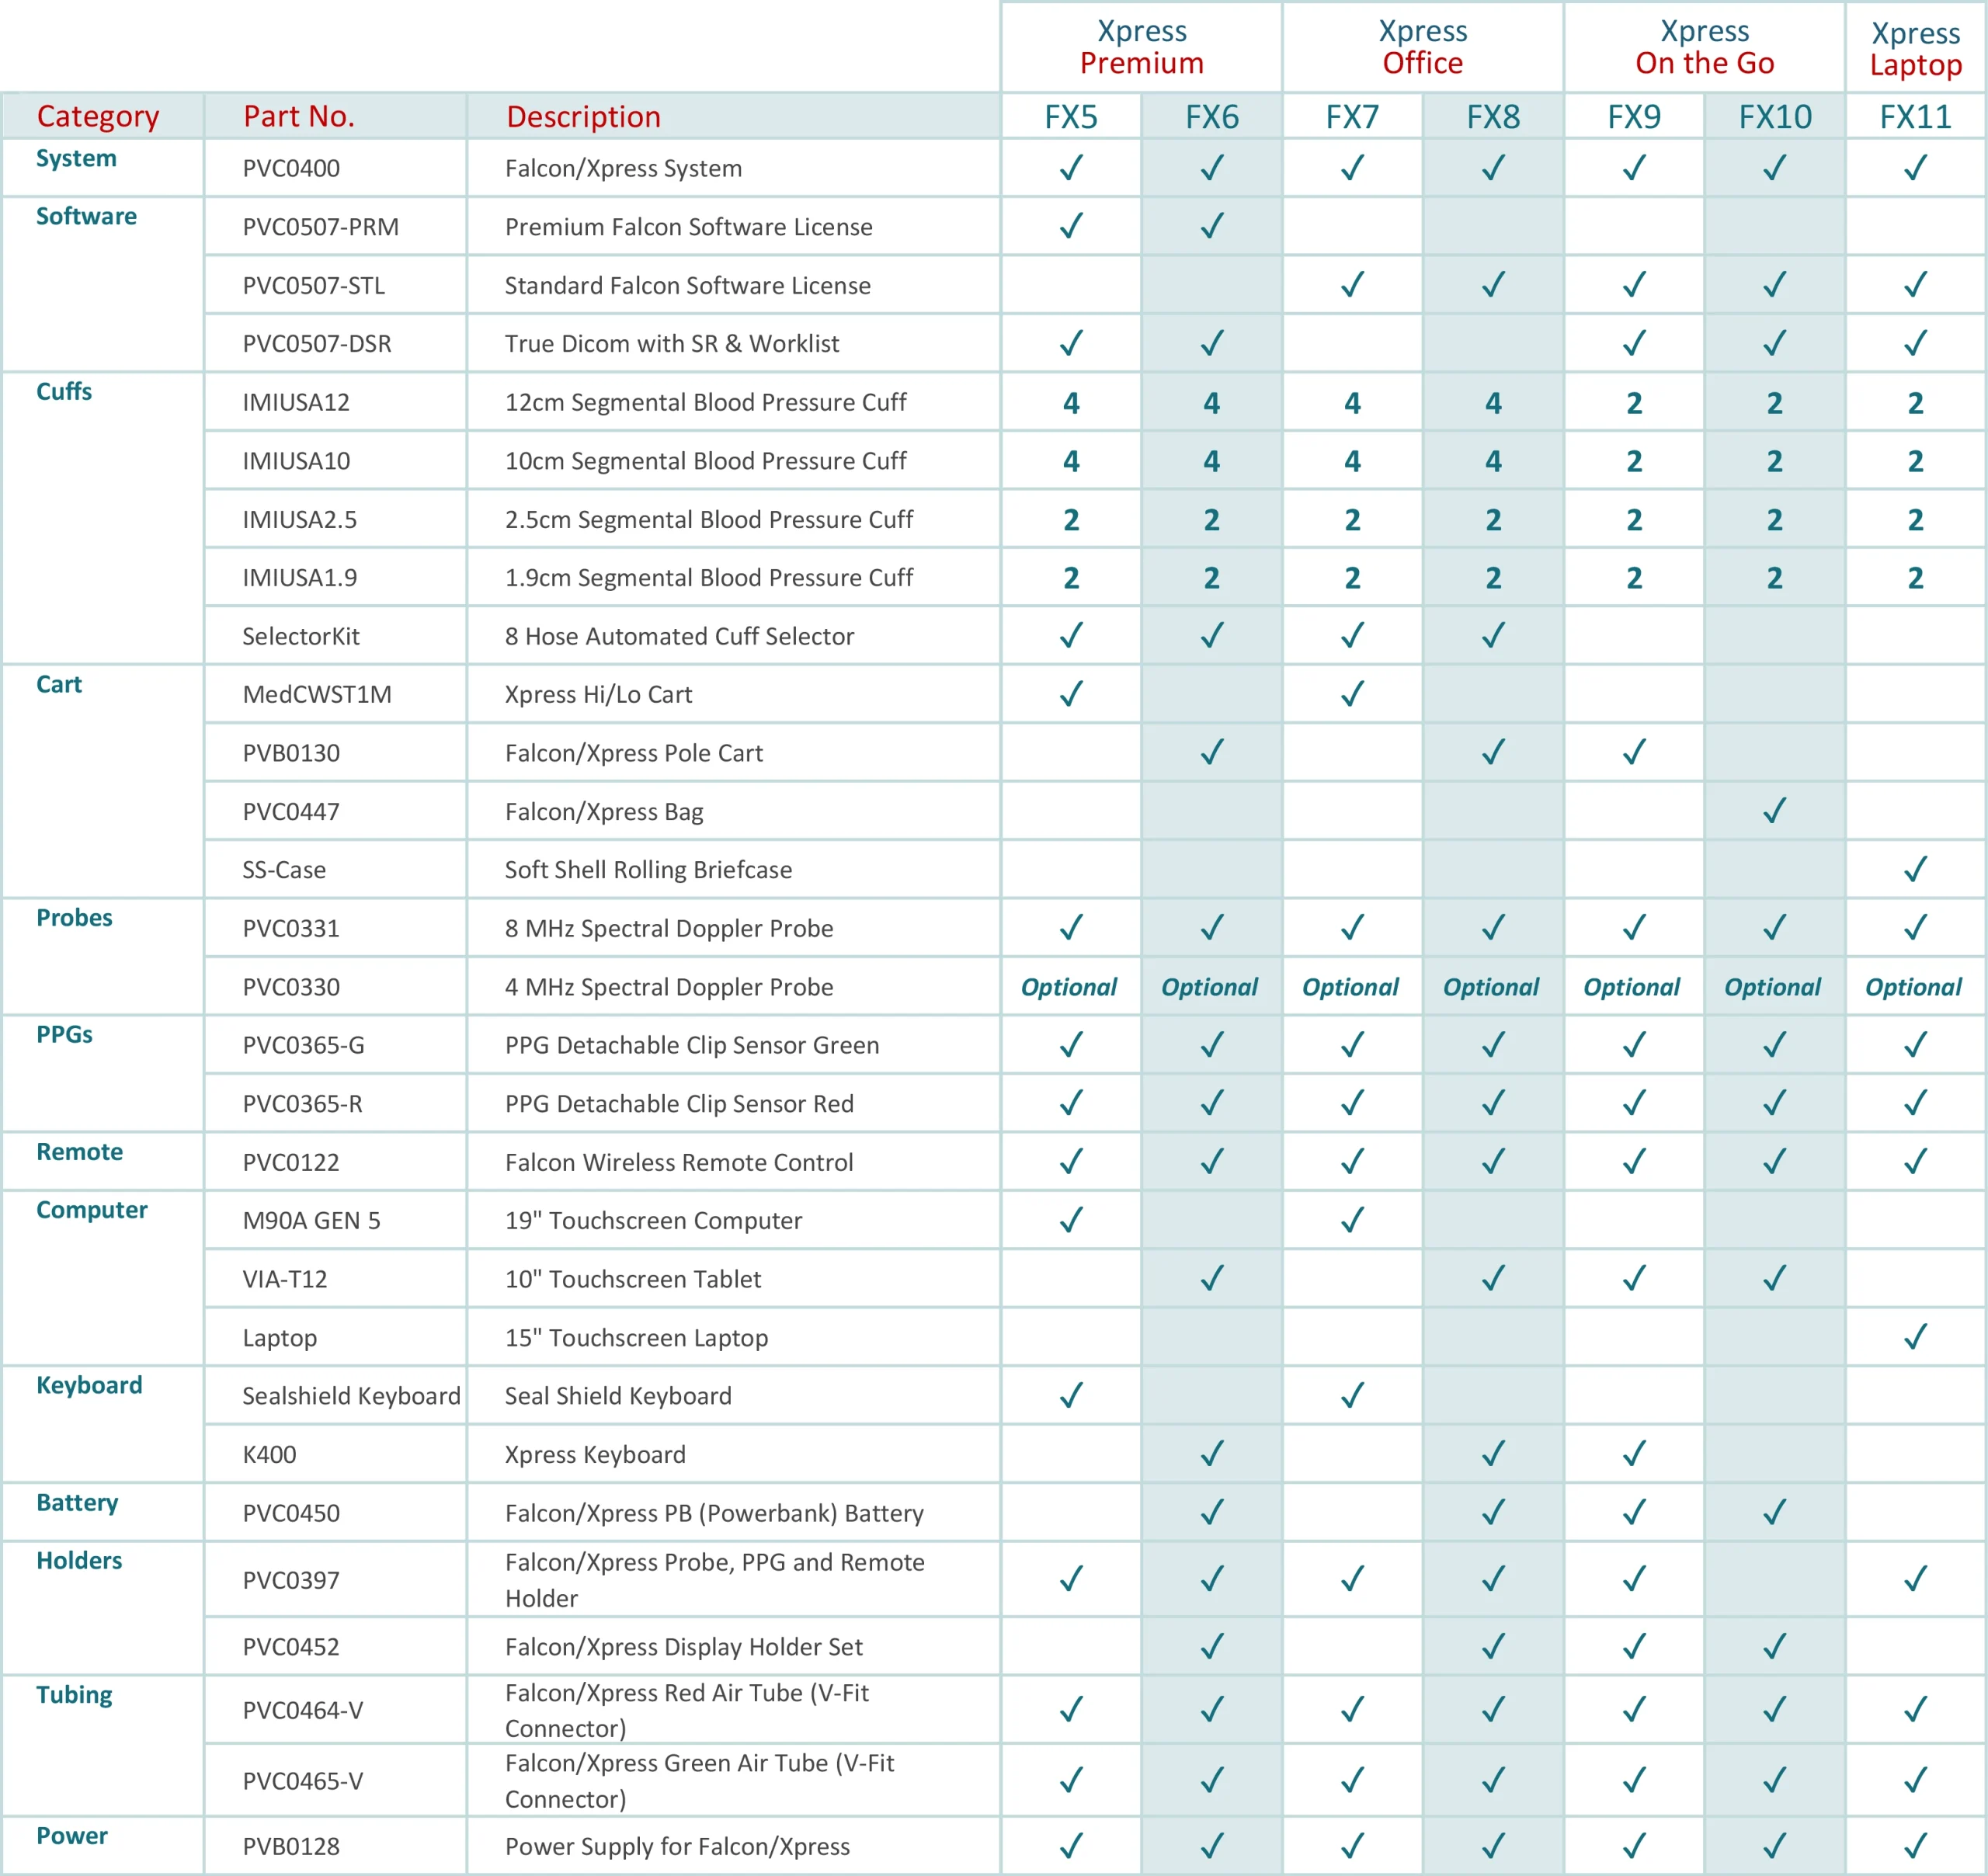
Download Falcon Xpress Comparison Chart

Key Features of the Falcon Xpress

8-Hose Automatic Cuff Selector

The Falcon Xpress features a built-in 8-hose automatic cuff selector that streamlines segmental testing by controlling cuff inflation and deflation without manual intervention. This intelligent system ensures accurate, consistent pressure delivery and saves valuable time during exams by improving efficiency, standardization, and patient comfort.
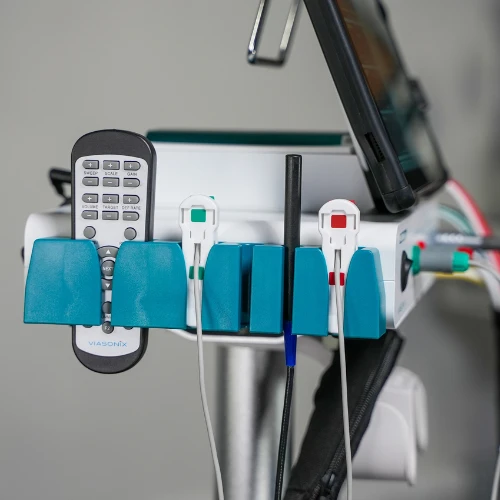
Everything in Reach

The Falcon Xpress is thoughtfully designed with convenience in mind. Probes, remotes, pens, and essential accessories are neatly stored and easily accessible right on the system. Whether you’re in a clinic or on the move, this organized layout ensures smooth workflow and quick transitions between patients.
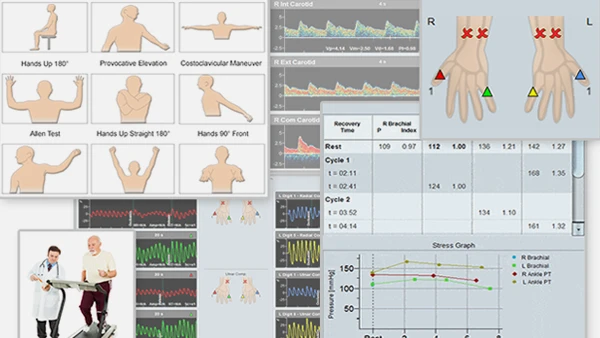
Comprehensive Vascular Testing

The Falcon Xpress supports a wide range of non-invasive vascular studies including ABI, TBI, segmental pressures, digit PPG, venous reflux, PWV, fistula steal, palmar arch, and more. This makes it an ideal all-in-one solution for any vascular lab or clinic performing peripheral vascular diagnostics.
Fully Customizable Protocols

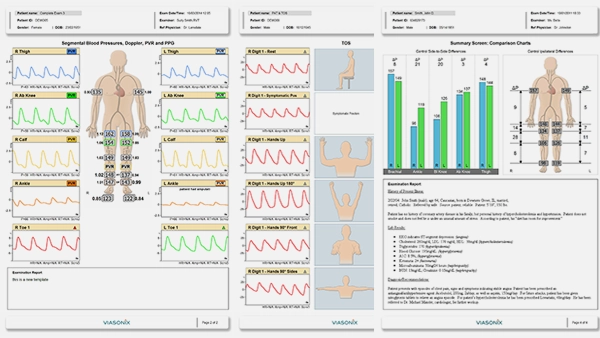
With Falcon’s premium software, you can design and modify test protocols to suit your specific clinical needs. Whether you’re standardizing exams across a large team or building research-specific workflows, Falcon Xpress gives you full flexibility and control.
Touchscreen Interface

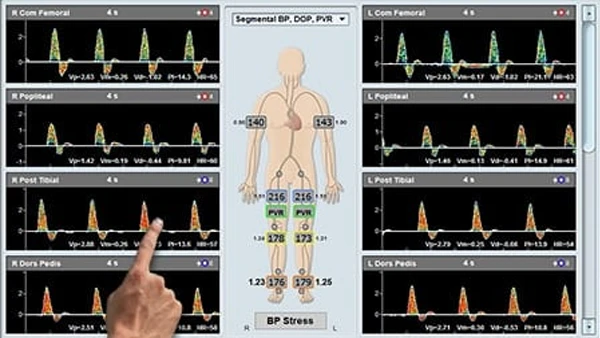
Designed with usability in mind, the Falcon Xpress features a sleek, intuitive touchscreen interface. Users can quickly navigate through protocols, view real-time waveforms, and input data with minimal training or setup time.
Spectral Doppler + UltraSense PPG

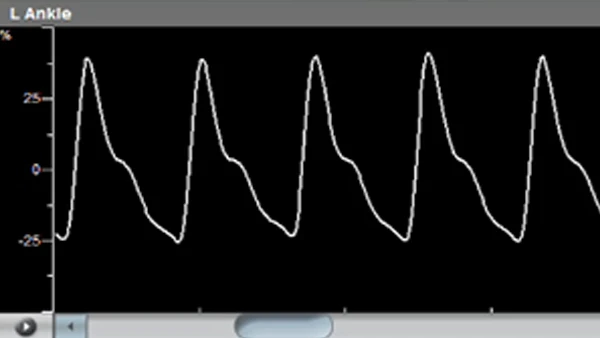
Each system includes an 8MHz spectral Doppler probe and two UltraSense PPG sensors with removable clips. This combination ensures high-fidelity waveforms and accurate physiologic measurements, even in challenging cases or distal studies.

DICOM & EMR Integration

The Falcon Xpress integrates seamlessly with your EMR and PACS systems using DICOM and HL7 standards. From automated worklists to structured reporting, your data flows smoothly from acquisition to documentation.

Built for Travel and On-the-Go

Whether you’re traveling between clinics, performing in-home diagnostics, or operating a mobile vascular lab, the system’s portable configurations and custom carrying cases make setup and transport effortless.

Supported in the USA

Every Falcon Xpress system is tested, and shipped from our facility in Buffalo, NY. Our team provides ongoing support, training, and service, ensuring your team is confident and your system always performs at its best.

Clinical Applications of the Falcon Xpress

Imagine what you would like to have in your ideal PVD system and discover it in the FALCON!
ABI, the Ankle Brachial Index, is the most popular application for fast and simple screening of a physiological vascular pathology. With this test pressure cuffs are placed on the 2 ankles and on 1 or 2 brachial segments.

The IMUSA FALCON/Pro allows to perform the ABI test with either Doppler or PPG sensors. In addition, the Falcon allows to perform simultaneous measurements in all sites under certain conditions for rapid measurements.

Prior to segmental cuff inflation, a reference signal is identified distal to the cuff location. When the cuff pressure exceeds the systolic pressure, the reference signal waveforms should disappear. Then, the cuff pressure is slowly deflated at constant bleeding rate, and the first occurrence of the return of the reference signal waveform marks the systolic pressure.

The ABI is defined as the ratio of the higher brachial pressure to each of the ankle pressures. A ratio of around 1 is considered normal, while lower values indicate various levels of significant peripheral arterial disease (PAD) according to international guidelines.

IMUSA Falcon PVD Clinical Applications – Ankle Brachial Index

Above is an example of a ABI test performed on a patient using IMUSA FALCON/Pro. The sensor used in this case is 8 MHz Doppler probe.

The Segmental Blood Pressure (SBP) tests require the placement of dedicated pressure cuffs on the various limb segments, which typically include the 2 brachial segments, the thighs (some protocols divide the thigh into 2 separate segments), the segment below the knees, the ankles and the toes.

Additional segments can be measured, such as the digits for diagnosis of the Raynaud’s Syndrome.

IMUSA Falcon PVD – Segmental Blood Pressures

Prior to segmental cuff inflation, a reference signal is identified distal to the cuff location. This reference signal is typically a CW Doppler measurement or a PPG (Photo-Plethysmograph, used for the digits and toes).

Above is an example of a SBP measurement taken from IMUSA FALCON/Pro system using 8 MHz CW Doppler probe.

When the cuff pressure exceeds the systolic pressure, the reference signal waveforms should disappear. Then, the cuff pressure is slowly deflated at constant bleeding rate, and the first occurrence of the return of the reference signal waveform marks the systolic pressure.

The clinician is normally interested in the ratio of the ankle systolic pressure to the brachial pressure (ABI – Ankle Brachial Index), or in significant pressure differences either in sequential segments or side-to-side differences for the same segment.

Peripheral vascular Doppler measurements are normally performed using CW (Continuous Wave) Doppler probes.

Different Probe frequencies are used depending on the target vessels: 4 or 8 MHz are used for larger and deeper vessels such as the Carotid, Femoral or Popliteal arteries, and higher 8 or 10 MHz are used for the smaller and shallower vessels such as the Dorsalis Pedis or Tibial arteries.

The main objective is to qualitatively examine the waveform shapes: a normal peripheral artery (not in the carotids) will show 3 phases during a cardiac cycle, a prominent early systolic forward flow, a late systolic reverse flow, followed by a small component of forward flow again. This signifies a healthy elastic artery. As the vessel becomes less elastic (for example due to diabetes), the third and/or second phase will disappear.

In addition, significantly high velocities may indicate the presence of a stenosis or some other obstruction to the blood flow.

The Pulse Volume Recording (PVR) test is a pneumo-plethysmographic test used for detection of the segmental volume changes in the limb which result from the flowing blood, as a function of the cardiac cycle.

Similar to the Segmental Blood Pressure (SBP) measurements, dedicated pressure cuffs are placed around all limb segments prior to initiating the test.

The cuffs are then inflated to a pressure that would occlude the venous return, yet will maintain the arterial flow un-obstructed. This pressure is typically 65 mmHg.

Once the cuff pressure is stabilized, the waveform signals which reflect the segmental volume changes can be recorded. The clinicians are normally interested in the qualitative shape of the waveforms: a “normal” PVR consists of a rapid systolic upstroke and a rapid downstroke with a prominent dicrotic notch.

With increasing arterial disease the PVR waveform becomes attenuated, the upstrokes and downstrokes are less prominent and the PVR amplitude decreases and ultimately becomes flat.

The Venous Reflux test is used to determine the competence of the superficial venous valves in the calves of the legs. This test is performed with a DC PPG sensor.

When performing Venous Reflux test, the patient is requested to sit upright with the legs not touching the ground. A Photo-plethysmograph (PPG) sensor is attached to the leg above the ankle in the region of the posterior tibial artery. When the DC signal reaches a steady state baseline, the patient is requested to perform multiple leg dorsiflexions which result in “pumping” of all of the venous blood. After the dorsiflexions the patient is requested to remain still, while the PPG DC signal returns back to the initial baseline.

Optionally, the test can be repeated with a cuff wrapped around a segment on the leg (thigh, above/below knee) acting as a tourniquet.

The duration from the end of the dorsiflexions (maximal signal change) until the signal return to baseline (VRT, Venous Recovery Time) indicates the status of the valves. A slow recovery time indicates competent valves, while a fast VRT would indicate a suspicion of valvular incompetency.

The Photo-plethysmograph (PPG) test detects changes in segmental blood volume, in a similar manner to the Pulse Volume Recording (PVR) test. The PPG technology, however, is different than the pressure-sensor based PVR technology.

With PPG, infra-red signals are transmitted to the skin and reflected back to the sensor, therefore PPG waveforms reflect local and rather shallow skin variations in blood flow.

Typical PPG measurement sites are the toes and digits, and interpretation of the signals is in a similar manner to the interpretation of the PVR waveforms.

In order to differentiate different vascular disorders, or to determine the functional severity of a stenosis, some of the tests described above are repeated after induced stress.

Typically, the patient will be requested to perform treadmill or similar activity, under the supervision of the examiner.

Most of the time the stress testing will include Segmental Blood Pressures, particularly at the ankles and brachials, and sometimes also Pulse Volume Recording (PVR) and CW Doppler measurements.

Segmental pressures are often measured at different post-stress times to determine also the recovery time from the stress effects. The clinician is particularly interested in identifying significant variants from the resting pressure indices and specifically changes in the Ankle-to-Brachial Index (ABI).

On the left side is an example of a Segmental Blood Pressure measurement with induced stress (exercise in this case) performed using IMUSA FALCON Pro. The table shows blood pressure measurements in pre-exercise and post-exercise conditions. It is common to take multiple measurements (cycles) in timed intervals after performing the induced stress. The stress graph on the left side shows the recovery of each measured segment starting with pre-stress conditions until the last post-stress cycle.

The Thoracic Outlet Syndrome test is conducted in order to determine the vascular role when the patient’s symptoms are indicative of perfusion loss or neurogenic causes.

This procedure tests for intermittent perfusion loss, particularly in the arms and hands.

Either Doppler, PVR or PPG sensors detect normal resting waveforms in the digits or hands and then the patient is instructed through a sequence of positions such as: Hands-up Test, Adson or Scalene Maneuver, Costoclavicular Maneuver, Allen Test, and Provocative Elevation Test.

The clinician tries to identify a position which significantly reduces perfusion to determine whether the symptoms originate from vascular causes.

Raynaud’s disease is a rare disorder of the blood vessels, usually in the fingers and toes. It causes the blood vessels to narrow when you are cold or feeling stressed.

When this happens, blood can’t get to the surface of the skin and the affected areas turn white and blue. When the blood flow returns, the skin turns red and throbs or tingles. In severe cases, loss of blood flow can cause sores or tissue death.

Primary Raynaud’s happens on its own. The cause is not known. There is also secondary Raynaud’s, which is caused by injuries, other diseases, or certain medicines.

The test is typically performed with PPG sensors attached to fingers as well as pressure cuffs in some cases for blood pressure measurement of each finger. PPG pulse is taken simultaneously from each finger at rest and after cold immersion.

An immediate measurement after cold immersion is critical so that the effect of the cold immersion is not lost. Therefore, a system such as the IMUSA FALCON Pro is recommended for Raynaud’s Syndrome test due to its ability to measure all 5 fingers simultaneously, immediately after cold immersion.

The patient lies in a supine position with the legs slightly elevated. A venous occluding cuff is placed on the thigh and a Pulse Volume Recording (PVR) pressure cuff is placed on the calve.

Initially, the cuff acting as a sensor is measured and a baseline is determined. Then the thigh cuff is inflated to occlude the venous return (around 60 mmHg) and the changes in the sensor signal are recorded. Once a plateau is reached, the occluding cuff is rapidly deflated. The sensor signal also quickly returns back to the initial baseline. The clinician then determines MVO and SVC based on the sensor signal to determine venous functionality.

The Reactive Hyperemia test is allowed only in certain countries.

Stress testing is frequently used in peripheral vascular diagnosis to differentiate between different vascular disorders, or to determine the functional severity of an arterial stenosis. Systolic pressures are measured before and after inducing vascular stress. While typically the patient is asked to perform a physical exercise such as exercise on a treadmill, sometimes the patients have difficulties in performing exercise.

In special cases, the reactive hyperemia test (RH) can replace the standard exercise tests and induce vascular stress. RH requires to inflate a pressure cuff in order to occlude the blood flow to the limb or segment of interest for up to several minutes, and then rapidly releasing the cuff pressure in order to generate the hyperemic effect.

It is crucial that a professional examiner will be present near the patient at all time, and immediately deflate the pressure cuffs when necessary.

Penile function or impotence test is used for determination of whether penile function disorders are of vascular nature.

The IMUSA FALCON Pro allows to use a variety of tests, including the simultaneous combination of different tests. Such tests include Doppler arterial measurements in the penile vessels, blood pressure measurements with a penile pressure cuff, and PVR or PPG waveform measurements.

The results of such tests can either identify a penile vascular problem, or eliminate vascular issues as the cause of impotence.

The Palmar Arch Test (PAT), also known as Allen’s Test, is used to assess collateral blood flow to the hand before harvesting the radial or ulnar artery. The test involves placing PPG sensors on two or more fingers, recording baseline waveforms, then observing changes during and after manual artery compression. A significant drop in blood flow suggests inadequate collateral circulation, indicating the artery should not be harvested. The Falcon system enhances this process by allowing multi-digit monitoring, automated markers, and visual waveform analysis.
Extracranial examination is performed with Doppler measurements in the carotid and other extracranial vessels. These measurements focus on the measurement of peak and mean blood flow velocities in order to identify a vascular obstruction to flow, such as an arterial stenosis.

The common blood vessels during extracranial evaluation are the common, internal and external carotid arteries, as well as the subclavian artery. A measurement at the location of a stenosis will result in increased blood flow velocities.

Falcon Accessories

Configure the Falcon for Your Clinical
Requirements With a Wide Range of
Accessories Available